Advanced coronary angiography procedures for accurate diagnosis of heart blockage, chest pain, and cardiovascular disease by Dr. Sarita Rao, Senior Interventional Cardiologist at Apollo Hospitals Indore.

Orbital Atherectomy in Indore

What is Orbital Atherectomy?

Orbital Atherectomy is an advanced minimally invasive coronary intervention used to treat severely calcified coronary artery blockages that cannot be effectively treated with conventional angioplasty alone.

The procedure uses a tiny diamond-coated crown that rotates at high speeds of up to 80,000 to 120,000 revolutions per minute (RPM). As the crown moves through the artery, it gently sands away hardened calcium deposits while preserving healthy vessel tissue.

Unlike some plaque modification techniques that primarily target surface calcium, Orbital Atherectomy can effectively modify both superficial and deep calcium deposits within the artery wall. This helps improve artery flexibility and allows safer, more effective stent placement.

Orbital Atherectomy is particularly beneficial in complex coronary artery disease where severe calcification may prevent proper balloon expansion or stent deployment.

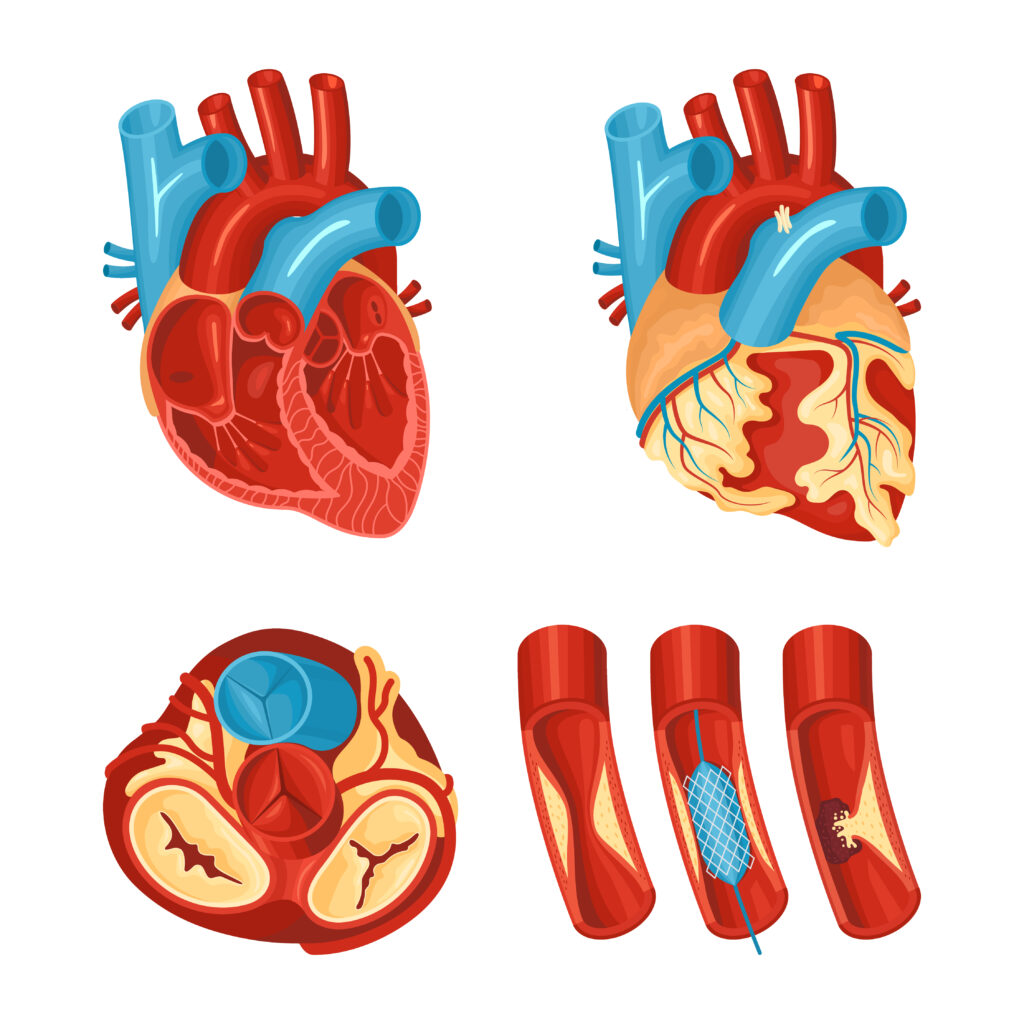
Orbital Atherectomy

Who May Need Orbital Atherectomy?

When is Orbital Atherectomy Recommended?

Orbital Atherectomy or Laser Atherectomy

Orbital Atherectomy may be recommended for patients with severe coronary artery calcification that makes standard angioplasty or stent implantation difficult.

Common Conditions Requiring Orbital Atherectomy

Early treatment of calcified coronary artery disease helps improve blood flow and reduces the risk of future cardiac complications.

Advanced Calcium Modification Therapy

Conditions Orbital Atherectomy Can Treat

Severe Coronary Artery Calcification

Breaks down hardened calcium deposits that restrict blood flow and complicate coronary interventions.

Severe Coronary Artery Calcification occurs when hardened calcium deposits build up within the coronary arteries, making them stiff and difficult to treat with conventional angioplasty. Advanced plaque-modification techniques such as rotablation, orbital atherectomy and intravascular lithotripsy (IVL) may be used in selected cases to modify the calcium and prepare the artery for balloon angioplasty and stent placement. Treatment is planned according to the severity, location and characteristics of the calcified lesion.

Complex Coronary Lesions

Treats difficult artery blockages where conventional balloons and stents may not perform effectively.

Complex Coronary Lesions are difficult coronary artery blockages that may be challenging to treat with standard balloons or stents alone. These lesions can involve severe calcification, long or diffuse blockages, chronic total occlusions or complex vessel anatomy. In selected patients, advanced techniques such as atherectomy, intravascular lithotripsy (IVL), specialized angioplasty and intravascular imaging may be used to prepare the artery and support effective stent placement. Treatment is tailored to the patient's coronary anatomy and clinical condition.

Stent Preparation Cases

Prepares heavily calcified arteries for successful stent implantation and optimal stent expansion.

Stent Preparation Cases involve advanced techniques used to prepare heavily calcified or complex coronary arteries before stent implantation. Plaque-modification methods such as rotablation, orbital atherectomy or intravascular lithotripsy (IVL) may be used to modify hardened calcium and improve vessel flexibility. Proper lesion preparation can facilitate stent delivery, expansion and apposition, helping achieve an effective treatment result in appropriately selected patients.

Deep & Superficial Calcium Deposits

Modifies calcium within multiple layers of the artery wall to improve vessel flexibility.
Deep & Superficial Calcium Deposits refer to calcium buildup within different layers of the coronary artery wall, which can make the vessel stiff and difficult to expand during angioplasty. Advanced calcium-modification techniques such as Intravascular Lithotripsy (IVL) can help modify both superficial and deeper calcium deposits, improving vessel flexibility and supporting more effective balloon angioplasty and stent expansion in selected patients.

High-Risk Coronary Interventions

Improves outcomes in patients with complex coronary anatomy and severe arterial calcification.
High-Risk Coronary Interventions are advanced procedures used to treat patients with complex coronary anatomy, severe arterial calcification, multiple blockages or other challenging lesions. Specialized techniques such as atherectomy, intravascular lithotripsy (IVL), advanced imaging and complex PCI strategies may be used to facilitate effective vessel preparation and stent implantation. Careful assessment and individualized treatment planning are essential to manage procedural risks and optimize outcomes in appropriately selected patients.

How Orbital Atherectomy is Performed

Step-by-Step Orbital Atherectomy Procedure

 Step 1: Preparation

The procedure is performed under local anesthesia with continuous cardiac monitoring

Step 2: Catheter Insertion

A thin catheter is inserted through the wrist or groin artery and guided toward the blocked coronary artery.

Step 3: Orbital Crown Positioning

The diamond-coated orbital crown is carefully positioned at the site of the calcified blockage.

Step 4: Calcium Modification 

The crown rotates at high speed, gently sanding away calcium deposits and improving artery compliance.

Step 5: Vessel Preparation

The artery becomes more flexible and suitable for further treatment.


Advantages of Orbital Atherectomy Treatment

Benefits of Orbital Atherectomy

  • Treats severely calcified coronary arteries
  • Modifies both deep and superficial calcium deposits
  • Improves stent expansion and placement
  • Increases angioplasty success rates
  • Minimally invasive treatment approach
  • Preserves healthy vessel tissue
  • Improves blood flow restoration
  • Reduces complications during coronary interventions
  • Short hospital stay
  • Faster recovery compared to surgical procedures

Risks & Safety Considerations

Is Orbital Atherectomy Safe?

Orbital Atherectomy is considered a safe and effective treatment option for selected patients with heavily calcified coronary artery disease when performed by experienced interventional cardiologists.

Although complications are uncommon, possible risks may include:

  • Minor bleeding or bruising
  • Blood vessel injury
  • Temporary heart rhythm disturbances
  • Artery dissection in rare cases
  • Contrast dye reaction
  • Temporary chest discomfort

Dr. Sarita Rao utilizes advanced orbital atherectomy technology, modern imaging systems, and evidence-based treatment protocols to maximize procedural safety and effectiveness.

Recovery & Aftercare Guidelines

Recovery After Orbital Atherectomy

Most patients recover quickly after Orbital Atherectomy and can gradually resume normal activities within a few days.

Recovery Recommendations

  • Follow prescribed medications carefully
  • Maintain blood pressure and cholesterol control
  • Avoid smoking and tobacco products
  • Follow a heart-healthy lifestyle
  • Stay physically active as advised
  • Attend scheduled cardiac follow-up visits

Long-term preventive cardiac care helps maintain healthy blood flow and reduces future coronary artery complications.

FAQs

Frequently Asked Questions

Orbital Atherectomy is used to treat heavily calcified coronary artery blockages that cannot be effectively managed with standard angioplasty alone.

Orbital Atherectomy uses an orbiting diamond-coated crown that treats both superficial and deep calcium deposits, while Rotablation uses a rotating burr to modify hardened plaque.

The procedure is performed under local anesthesia and most patients experience minimal discomfort.

Yes. By modifying calcium deposits and increasing artery flexibility, Orbital Atherectomy helps improve stent expansion and long-term outcomes.

Yes. It is a minimally invasive treatment option that can be safely performed in selected elderly patients with severe calcified coronary artery disease.

The procedure typically takes between 1 and 2 hours depending on the complexity of the blockage.

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast

Far far away, behind the word mountains, far from the countries Vokalia and Consonantia, there live the blind texts. Separated they live in Bookmarksgrove right at the coast